
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Other
Top videos


Hemodialysis is the process of cleaning the patient’s blood outside the body. Learn more about this renal replacement therapy option.
Read more: http://www.freseniusmedicalcar....e.com/en/patients-fa

Knee replacement involves replacing a knee joint that has been damaged or worn away, usually by arthritis or injury. Find out more here: https://www.bupa.co.uk/health-....information/knee-cli

When a ventral hernia occurs, it usually arises in the abdominal wall where a previous surgical incision was made. In this area the abdominal muscles have weakened; this results in a bulge or a tear. In the same way that an inner tube pushes through a damaged tire, the inner lining of the abdomen pushes through the weakened area of the abdominal wall to form a balloon-like sac. This can allow a loop of intestines or other abdominal contents to push into the sac. If the abdominal contents get stuck within the sac, they can become trapped or “incarcerated.” This could lead to potentially serious problems that might require emergency surgery.

Hip examination by Harvard medical school

technique of combined cataract surgery and glaucoma tube shunt using triamcinolone to verify fluid outflow
Very Hard White Cataract with trypan blue "Vision blue" Capsule Staining
how to obtain intravenous access through cutting down over a large peripheral vein
Inspection of the mouth

Henry Anhalt DO FAAP
Ped Eddo
This video shows the process of development and growth of the fetus intrauterine.
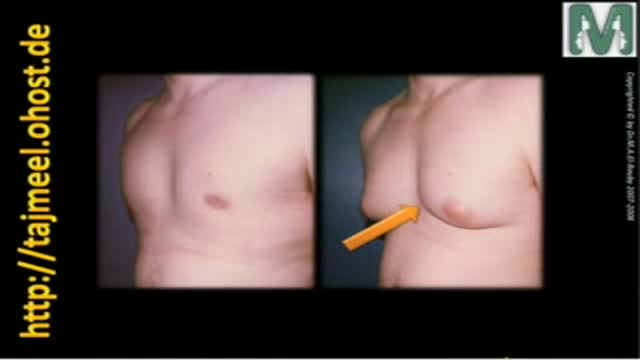
Gynecomastia means enlargement of male breast to resample female breast that is a common problem between males and causes many psychological problem
Dr. Mohamed El-Rouby
Consltant of Plastic surgery - Faculty of Medicine - Ain Shams University
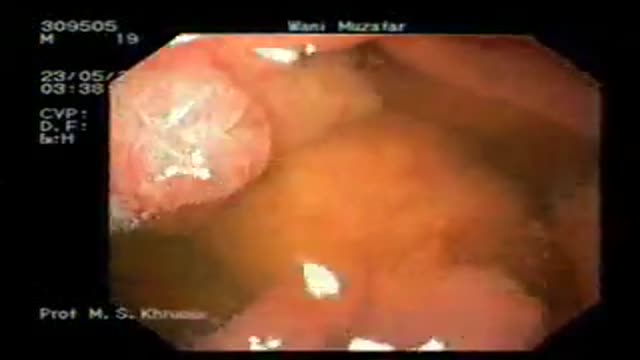
ENDOSCOPIC (NON-SURGICAL) REMOVAL OF MULTIPLE LARGE TUMORS FROM STOMACH IN A PATIENT WITH PEUTZ-JEGHERS SYNDROME
PEUTZ-JEGHERS SYNDROME: Peutz-Jeghers syndrome (PJS) is a familial syndrome consisting of mucocutaneous pigmentation, gastrointestinal polyposis and cancers of gut & other sites like breast, ovary, and testes. PJS has an autosomal dominant inheritance with variable and incomplete penetrance. Germline mutations of STK11/LKB1 gene on 19p cause this syndrome. Mucocutaneous pigmentation may be noted in early infancy. These deposits of melanin are most commonly found around the mouth, nose, lips, buccal mucosa, hands, and feet, and may also be present in perianal and genital areas. PJS polyps may be found in stomach, small intestine, or colon, but they tend to be prominent in the small intestine. These polyps may increase in size and cause small intestinal obstruction or intussusceptions that may occur in early infancy. Acute upper gastrointestinal bleeding and chronic faecal blood may complicate the disease.
PATIENT: The patient was a 25 yr male who had mucocutaneous pigmentation and multiple polyps in the stomach and duodenum. He presented with bleeding from gastric polyps. As the polyps in stomach were numerous, (more than 20 in number) and were large in size (some equal to small egg size), he had been advised to undergo surgery. Surgery planned was total gastrectomy.
PROCEDURE: The patient underwent video-endoscopy of the esophagus, stomach and duodenum. All polyps were examined for size and presence or absence of stalk. A plan to remove all the gastric polyps at endoscopy was made in the same sitting. He received light conscious sedation. Flat polyps were raised form the gastric wall by injection of saline in to polyp base to let these lesions have a stalk. This was done by needle injector. Each polyp was engaged in a snare and the polyp stalk was cut by coagulation cutting current. The cuts were clean without any bleeding. All polyps were recovered for histology. The histology revealed all polyps to be hamartomous lesions. None of the polyps were cancerous. Patient has been followed up for over one year and is doing fine without any further bleeding or pain.
Video shows the procedure of videoendoscpy and endoscopic removal of polyps.
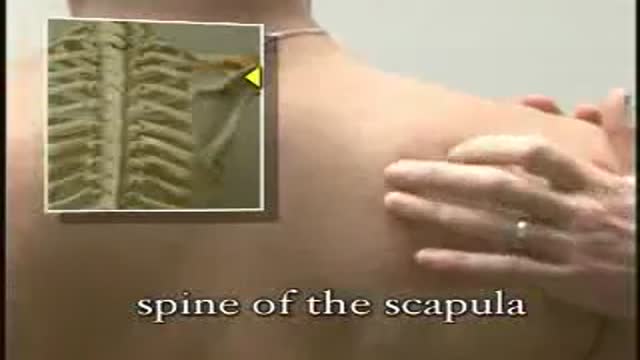
Examination of the upper limb by Loyola medical school, Chicago Part 2

Part 2: from Loyola Medical School, Chicago showing clinical examination of the neurological system.

One Handed Surgical Knot
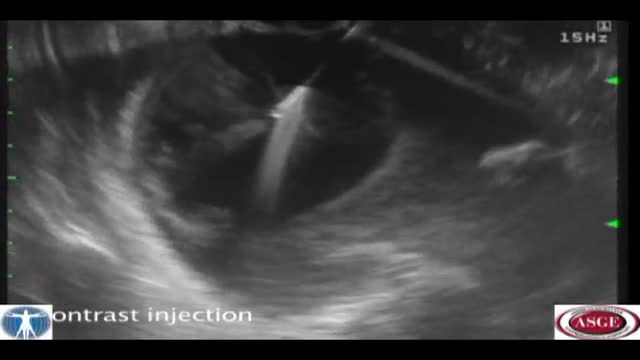
Pancreatic pseudocyst drainage was the first therapeutic application of EUS. The cyst is punctured under ultrasound guidance, contrast injected, and a guidewire inserted. Initial dilation to 8mm is performed over the wire The EUS scope is then exchanged over the wire for a forward viewing endoscope.... A second dilation to 18mm is performed. This enables entry of the endoscope into the cyst perform cystoscopy, debridement if necessary, and insertion of multiple large bore double pigtail stents. The curved linear array-or CLA—echoendoscope has oblique viewing optics located proximal to an oblique scanning transducer. The accessory exits from the shaft of the echoendoscope at an ablique angle, adjustable between 15 and 30 degrees. There are several technical limitations using this echoendoscope. The oblique angle of exit results in a weekend transfer of force when advancing the accessory, difficult deployment of larger bore accessories, and in instrument tunneling effect relative to the bowel wall. There is the potential loss of access during endoscope exchange. A novel CLA echoendoscope was developed by the Olympus Corporation that shifts the orientation of endoscopic and ultrasound views from oblique to forward viewing. The channel is therapeutic at 3.7mm Note that the working channel is located adjacent to the ultrasound transducer at the endoscope tip. The accessory exits the working channel in the axis of the shaft. Shown here are balloon inflation and deployment of a Dormia basket. We report on the use of the prototype forward viewing echoendoscope in six consecutive patients who were referred for pancreatic cyst drainage. Here you see endoscopic view-indistinguisable from that of a gastroscope-showing a bulge where the cyst impinges against the posterior gastric wall. Power Doppler is switched on and highlights multiple vessels interposed in the wall This allows selection of a safe vessel-free window for a cyst puncture A 19 G needle is advanced into the cyst lumen. A sample of contents is aspirated for fluid analysis. A guidewire under ultrasound guidance into the cyst. An 18mm balloon is coaxially thread over the wire and advanced across the cyst wall, Note that resistance is encountered, but the forward transfer of force overcome this. The dilation is performed under forward viewing endoscopuc and ultrasound guidance. As the balloon is maximally inflated we see the cystgastrostomy open up. The balloon is then deflated while simultaneously advancing the scope into the cyst cavity. Cystoscopy isnow performed showing the cyst contents to be filled with pasty wall-adherent necroses. Pulsed power Doppler is switched on we can see and hear arterial flow vessels within the wall of the cyst. This identifies sensitive areas at bleeding risk when performing debridement In this case vigorous water jet irrigation is performed through an accessory water irrigation channel built into the echoendoscope. This issued to clear nonadherent debris. Our experience has shown that it is not necessary to actively remove wall-adherent debris using extraction tools as such Dormia or Roth net basket to achieve cyst resolution. Three large bore 10 Fr double pigtail stents are now inserted into the cyst under direct endoscopic guidance. The first stent is delivered over a guide catheter. The second stent. And the third stent All three stents are deployed. Finally, a nasocystic catheter is inserted for maintenance irrigation. In another patient we used the Cook Cystome to perform cystgastrostomy. We have found the Cystotome easy to delivery through the forward viewing echoendoscope. As shown, we advance the Cystotome into the cyst while applying diathermy. This is performed under and endoscopic guidance, entering the cyst at a near perpendicular orientation. After entry, the Cystotome is removed and cyst fluid gushes from the cystagastrotomy site.

Extradural approach via Orbito-Zygomatic Craniotomy

IM Injection instructions

Allograft material is placed submucosally to expand tissue to simulate turbinate tissue. It is placed in a location to direct the airstream toward "virgin" tissue that can sense airflow. Empty Nose Syndrome (ENS) is an iatrogenic disease characterized by paradoxical obstruction: a hugely patent no...
se with subjective "blockage" or poor nasal breathing.
Treatment of bowel injury by IUD
