
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Other
Top videos

Memory Loss & the Brain. It's not just a movement disorder. Besides causing tremors and other motion-related symptoms, Parkinson's disease affects memory, learning, and behavior. Parkinson's disease is notorious for so-called motor symptoms like muscle rigidity, tremor, slowed movement, and unsteady posture and gait.
6 987 24 MORE How Does Anesthesia Work? Credit: itsmejust | Shutterstock If you’ve ever had surgery, unless you are super tough, you’ve gone through it with the benefit of anesthetics. But, how do these body-numbing elixirs work? Prior to the invention of anesthesia in the mid-1800s, surgeons had to hack off limbs, sew up wounds and remove mysterious growths with nothing to dull the patient's pain but opium or booze. While these drugs may have numbed the patient, they didn’t always completely block the pain, or erase the memory of it. Since then, doctors have gotten much better at putting us out with drug combinations that ease pain, relax muscles and, in some cases, put us in a deep state of hypnosis that gives us temporary amnesia. Today, there are two primary types of anesthesia drugs: those that knockout the whole body (general) and those that only numb things up locally.

On the day of your surgery, your health care team will take you to a preparation room. Your blood pressure and breathing will be monitored. You may receive an antibiotic medication through a vein in your arm. You will then be taken to an operating room and positioned on a table. You'll be given a general anesthesia medication to put you in a sleep-like state so that you won't be aware during your operation. The surgical team will then proceed with your colectomy. Colon surgery may be performed in two ways: Open colectomy. Open surgery involves making a longer incision in your abdomen to access your colon. Your surgeon uses surgical tools to free your colon from the surrounding tissue and cuts out either a portion of the colon or the entire colon. Laparoscopic colectomy. Laparoscopic colectomy, also called minimally invasive colectomy, involves several small incisions in your abdomen. Your surgeon passes a tiny video camera through one incision and special surgical tools through the other incisions. The surgeon watches a video screen in the operating room as the tools are used to free the colon from the surrounding tissue. The colon is then brought out through a small incision in your abdomen. This allows the surgeon to operate on the colon outside of your body. Once repairs are made to the colon, the surgeon reinserts the colon through the incision. The type of operation you undergo depends on your situation and your surgeon's expertise. Laparoscopic colectomy may reduce the pain and recovery time after surgery. But not everyone is a candidate for this procedure. Also, in some situations your operation may begin as a laparoscopic colectomy, but circumstances may force your surgical team to convert to an open colectomy. Once the colon has been repaired or removed, your surgeon will reconnect your digestive system to allow your body to expel waste. Options may include: Rejoining the remaining portions of your colon. The surgeon may stitch the remaining portions of your colon together, creating what is called an anastomosis. Stool then leaves your body as before. Connecting your intestine to an opening created in your abdomen. The surgeon may attach your colon (colostomy) or small intestine (ileostomy) to an opening created in your abdomen. This allows waste to leave your body through the opening (stoma). You may wear a bag on the outside of the stoma to collect stool. This can be permanent or temporary. Connecting your small intestine to your anus. After removing both the colon and the rectum (proctocolectomy), the surgeon may use a portion of your small intestine to create a pouch that is attached to your anus (ileoanal anastomosis). This allows you to expel waste normally, though you may have several watery bowel movements each day. As part of this procedure, you may undergo a temporary ileostomy.
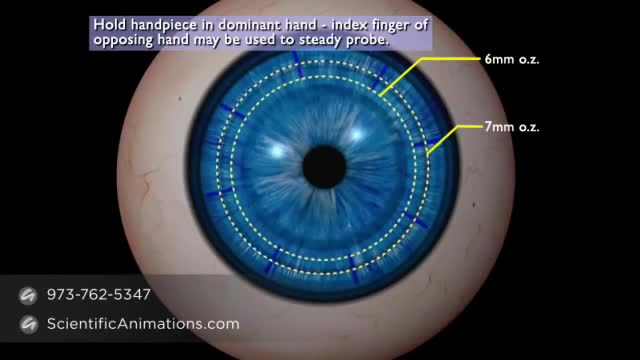
Keratoplasty is the procedure whereby abnormal corneal tissue is replaced by a healthy donor cornea.
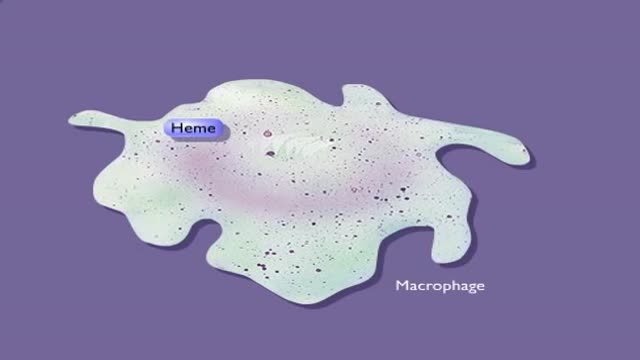
Red blood cells, which form one of the major constituents of blood, are characterized by the absence of nuclei, hence they are unable to undergo cellular division or generate new erythrocytes from old ones. This eventually leads to cell disintegration, which typically occurs 4 months after the fully developed red blood cells have been in circulation within the bloodstream. During the degeneration of the red blood cells, some components of the hemoglobin are excreted from the body while other parts are conserved.
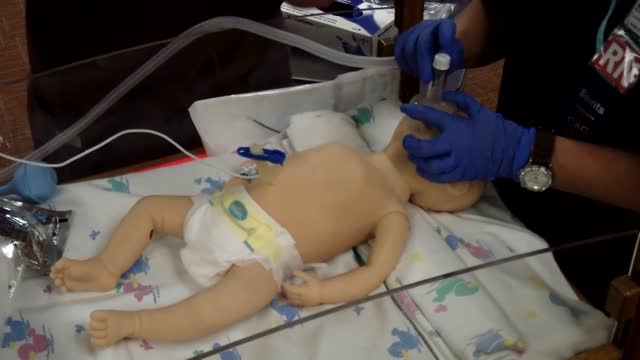
Neonatal resuscitation skills are essential for all health care providers who are involved in the delivery of newborns. The transition from fetus to newborn requires intervention by a skilled individual or team in approximately 10% of all deliveries. This figure is concerning because 81% of all babies in the United States are born in nonteaching, nonaffiliated level I or II hospitals. In such hospitals, the volume of delivery service may not be perceived as sufficient economic justification for the continuous in-hospital presence of personnel with high-risk delivery room experience, as recommended by the American Academy of Pediatrics (AAP) and the American College of Obstetricians and Gynecologists (ACOG). [1] Perinatal asphyxia and extreme prematurity are the 2 complications of pregnancy that most frequently necessitate complex resuscitation by skilled personnel. However, only 60% of asphyxiated newborns can be predicted ante partum. The remaining newborns are not identified until the time of birth. Additionally, approximately 80% of low-birth-weight infants require resuscitation and stabilization at delivery. Nearly one half of newborn deaths (many of which involve extremely premature infants) occur during the first 24 hours after birth. Many of these early deaths also have a component of asphyxia or respiratory depression as an etiology. For the surviving infants, effective management of asphyxia in the first few minutes of life may influence long-term outcome. Even though prenatal care can identify many potential fetal difficulties ante partum, allowing maternal transfer to the referral center for care, many women who experience preterm labor are not identified prospectively and therefore are not appropriately transferred to a tertiary perinatal center. Consequently, many deliveries of extremely premature infants occur in smaller hospitals. For this reason, all personnel involved in delivery room care of the newborn should be trained adequately in all aspects of neonatal resuscitation. Additionally, equipment that is appropriately sized to resuscitate infants of all gestational ages should be available in all delivering institutions, even if the institution does not care for preterm or intensive care infants. Along with the necessary skills, the practitioner should approach any resuscitation with a good comprehension of transitional physiology and adaptation, as well as an understanding of the infant's response to resuscitation. Resuscitation involves much more than possessing an ordered list of technical skills and having a resuscitation team; it requires excellent assessment skills and a grounded understanding of physiology.

Marfan syndrome is a genetic disorder that affects the body’s connective tissue. Connective tissue holds all the body’s cells, organs and tissue together. It also plays an important role in helping the body grow and develop properly. marfan_general_2.jpg What is Marfan Syndrome?Connective tissue is made up of proteins. The protein that plays a role in Marfan syndrome is called fibrillin-1. Marfan syndrome is caused by a defect (or mutation) in the gene that tells the body how to make fibrillin-1. This mutation results in an increase in a protein called transforming growth factor beta, or TGF-β. The increase in TGF-β causes problems in connective tissues throughout the body, which in turn creates the features and medical problems associated with Marfan syndrome and some related disorders. Because connective tissue is found throughout the body, Marfan syndrome can affect many different parts of the body, as well. Features of the disorder are most often found in the heart, blood vessels, bones, joints, and eyes. Some Marfan features – for example, aortic enlargement (expansion of the main blood vessel that carries blood away from the heart to the rest of the body) – can be life-threatening. The lungs, skin and nervous system may also be affected. Marfan syndrome does not affect intelligence.
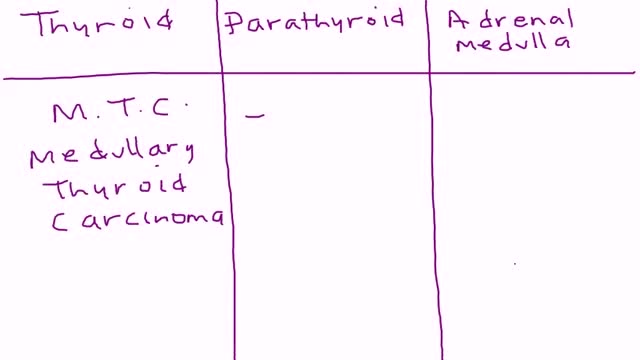
Multiple endocrine neoplasia type 2 (MEN2) (also known as "Pheochromocytoma and amyloid producing medullary thyroid carcinoma", "PTC syndrome," and "Sipple syndrome") is a group of medical disorders associated with tumors of the endocrine system. The tumors may be benign or malignant (cancer).
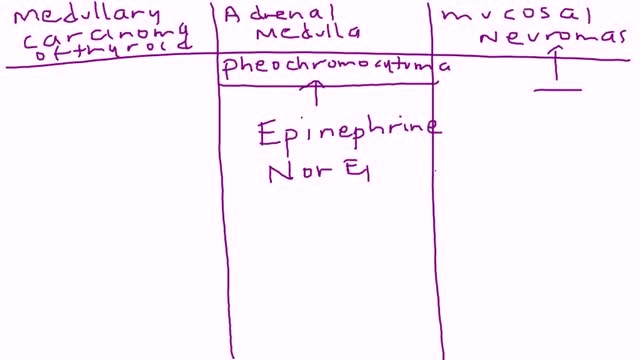
Multiple endocrine neoplasia type 2 (MEN2) is a hereditary condition associated with three primary types of tumors: medullary thyroid cancer, parathyroid tumors, and pheochromocytoma. MEN2 is classified into three subtypes based on clinical features. MEN2A, which affects 60% to 90% of MEN2 families Medullary thyroid cancer: 98% to 100% with MEN2A are affected Pheochromocytoma, a typically benign (noncancerous) tumor of the adrenal glands: 50% with MEN2A affected Parathyroid adenoma (benign tumor) or hyperplasia, meaning increased size, of the parathyroid gland: 5% to 10% with MEN2A affected MEN2B, which affects 5% of MEN2 families Medullary thyroid cancer: 98% to 100% with MEN2B affected Pheochromocytoma: 50% with MEN2B affected Mucosal neuromas, which is a benign tumor of nerve tissue on the tongue, lips and throughout the gastrointestinal tract: 95% to 98% affected Digestive problems caused by disordered nerves in the gastrointestinal tract: 75% to 90% affected Muscle, joint, and spinal problems: 95% affected Typical facial features, including swollen lips and thick eyelids: 75% to 90% affected Familial medullary thyroid cancer (FMTC), which affects 5% to 35% of MEN2 families Medullary thyroid carcinoma only Sources: Gagel RF, Marx SJ. “Multiple endocrine neoplasia.” Williams Textbook of Endocrinology, Chapter 40, 11th ed., Philadelphia, 2008, and Eng C, Clayton D, et al. Grubbs EG, Gagel RF. My, How Things Have Changed in Multiple Endocrine Neoplasia Type 2A! J Clin Endocrinol Metab 100(7):2532-5, 7/2015. PMID: 26151398. What causes MEN2? MEN2 is a genetic condition. This means that the cancer risk and other features of MEN2 can be passed from generation to generation in a family. The gene associated with MEN2 is called RET. A mutation (alteration) in the RET gene gives a person an increased risk of developing medullary thyroid cancer and other tumors associated with MEN2.

Warfarin is an anticoagulant medication - it is used to slow down the blood-clotting process. Anticoagulants are used to prevent blood clots which may cause vein blockages, heart attack and stroke. Warfarin is known under the brand names Warfant, Jantoven, Coumadin, Lawarin, Marevan, and Waran.
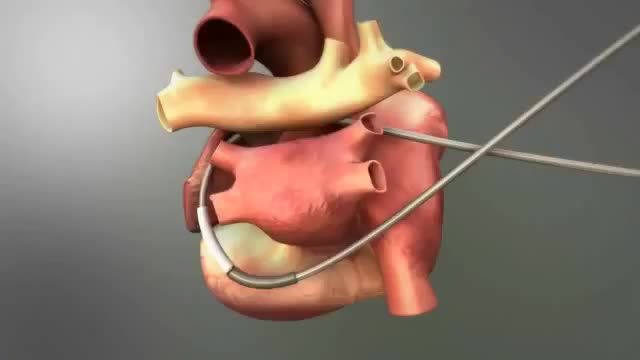
The Estech COBRA Fusion™ 150 Surgical Ablation System combines intuitive, real-time TCRF (Temperature Controlled Radiofrequency) energy control with proprietary Versapolar technology. Versapolar™ energy delivery is the first of its kind—an adaptable and effective platform that can deliver both bipolar and monopolar energy so that surgeons can easily and efficiently create reproducible transmural lesions with more flexibility, confidence and control.

Sliced Fingertip Makeup Tutorial

How to Grow a New Fingertip

This medical animation illustrates how acute myeloid leukemia (AML), the most common type of cancer in adults, develops in the blood and bone marrow. The narrator also discusses the symptoms of AML and AML treatment options.

How do you know if you have an STD? There’s only one way — you have to get tested. How do they test for STDs? Here’s the good news: STD testing is usually quick and painless. Get answers to all your questions about how to get tested for STDs.
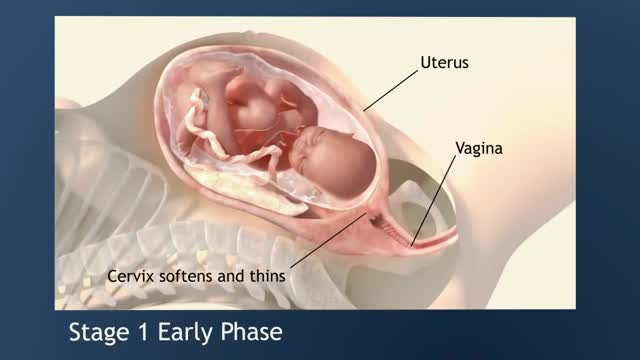
Early labour contractions usually feel like period pain, or you might experience a lower backache at 20 to 30 minute intervals. Sometimes these pains radiate from back to front, or vice versa. There's no need to start timing the contractions straight away – if they are mild contractions, ignore them. The first stage of labor is the longest and involves three phases: Early Labor Phase –The time of the onset of labor until the cervix is dilated to 3 cm. Active Labor Phase – Continues from 3 cm. until the cervix is dilated to 7 cm. Transition Phase – Continues from 7 cm. until the cervix is fully dilated to 10 cm.

Breastfeeding attachment Attaching your baby at the breasT

Twins in the Womb - Human Development

Hypertrophic pyloric stenosis (HPS) causes a functional gastric outlet obstruction as a result of hypertrophy and hyperplasia of the muscular layers of the pylorus. In infants, HPS is the most common cause of gastric outlet obstruction and the most common surgical cause of vomiting.

Dementia is not a specific disease. It's an overall term that describes a wide range of symptoms associated with a decline in memory or other thinking skills severe enough to reduce a person's ability to perform everyday activities. Alzheimer's disease accounts for 60 to 80 percent of cases. Vascular dementia, which occurs after a stroke, is the second most common dementia type. But there are many other conditions that can cause symptoms of dementia, including some that are reversible, such as thyroid problems and vitamin deficiencies.
