
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Other
Top videos

Here are seven ways to start reining in your risks today, before a stroke has the chance to strike. Lower blood pressure. ... Lose weight. ... Exercise more. ... Drink — in moderation. ... Treat atrial fibrillation. ... Treat diabetes. ... Quit smoking.
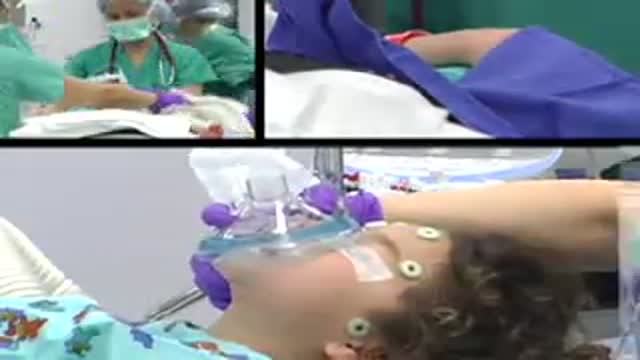
Watch as Dr. Benjamin Carson performs risky brain surgery on young Payton to remove a brain tumor. Dr. Carson, director of pediatric neurosurgery, is just one of the many reasons why Johns Hopkins Children's Center was recently ranked #1 in neurology and neurosurgery in America's Best Children's Hospitals 2008
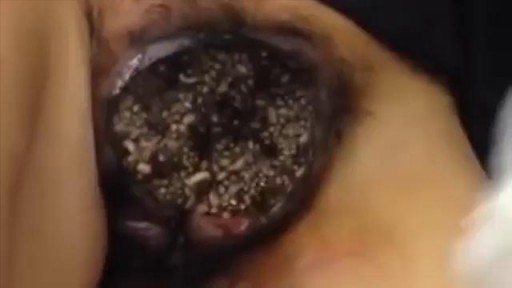
Watch that video of Nasty Female Genital Infection
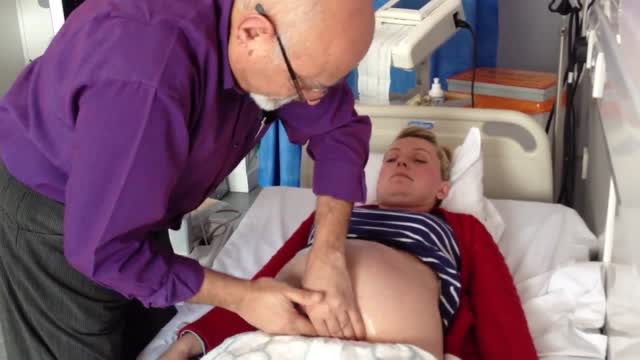
Successful External Cephalic Version (ECV) - Turning a breech baby in just 2 minutes!

Traumatic penile injury can be due to multiple factors. Penile fracture, penile amputation, penetrating penile injuries, and penile soft tissue injuries are considered urologic emergencies and typically require surgical intervention. The goals of treatment for penile trauma are universal: preservation of penile length, erectile function, and maintenance of the ability to void while standing. Traumatic injury to the penis may concomitantly involve the urethra.[1, 2] Urethral injury and repair is beyond the scope of this article but details can be found in Urethral Trauma. Penile fracture Penile fracture is the traumatic rupture of the corpus cavernosum. Traumatic rupture of the penis is relatively uncommon and is considered a urologic emergency.[3] Sudden blunt trauma or abrupt lateral bending of the penis in an erect state can break the markedly thinned and stiff tunica albuginea, resulting in a fractured penis. One or both corpora may be involved, and concomitant injury to the penile urethra may occur. Urethral trauma is more common when both corpora cavernosa are injured.[4] Penile rupture can usually be diagnosed based solely on history and physical examination findings; however, in equivocal cases, diagnostic cavernosography or MRI should be performed. Concomitant urethral injury must be considered; therefore, preoperative retrograde urethrographic studies should generally be performed. See the images below.

Full examination of the female from head to toe by Loyola Medical School, Chicago part 1

https://bit.ly/3HIStRc #shorts
Tracheotomy and tracheostomy are surgical procedures that create an opening in the trachea (windpipe) to help patients breathe when they have difficulty doing so through the nose or mouth. Though they are similar in purpose, there are some key differences between them.
Tracheotomy is a temporary procedure that involves creating a small incision in the trachea to insert a breathing tube. The tube is typically removed once the patient no longer requires it, and the incision heals on its own. Tracheostomy, on the other hand, is a more permanent solution that involves creating a hole in the trachea and inserting a tracheostomy tube, which remains in place for an extended period.
Indications for these procedures include:
Airway obstruction due to trauma, tumors, or infection
Severe respiratory distress or failure
Prolonged mechanical ventilation
Inability to protect the airway due to neurological disorders or impaired consciousness
Steps for performing a tracheotomy and tracheostomy:
Preparation: The patient is positioned, and the neck area is cleaned and draped. Local anesthesia is often administered, although general anesthesia may be used in some cases.
Incision: A small incision is made in the neck, and the muscles and tissues are carefully separated to expose the trachea.
Tracheal opening: A small opening is made in the trachea, typically between the second and third tracheal rings.
Tube insertion: A tracheotomy tube is inserted through the incision and into the trachea for a tracheotomy, while a tracheostomy tube is inserted for a tracheostomy. Both tubes are secured in place.
Confirmation: Proper placement of the tube is confirmed by listening for breath sounds and checking for adequate ventilation.
Pre-operative care typically involves a thorough assessment of the patient's medical history, as well as any necessary imaging studies or lab tests to ensure the procedure is appropriate and safe. Informed consent should be obtained from the patient or their legal representative.
Post-operative care includes monitoring the patient's vital signs, ensuring the tube remains secure and patent, and managing any pain or discomfort. For tracheostomy patients, regular cleaning and maintenance of the stoma (the opening in the trachea) and the tracheostomy tube are essential to prevent infection and other complications. Long-term care may involve speech therapy, respiratory therapy, and support from a multidisciplinary team to address any ongoing needs.
It's crucial to remember that these procedures should only be performed by trained medical professionals in a clinical setting.
for additional information about this procedure check our article @ www.medicalartsshop.com
For more free resources, find us on Pinterest & Facebook pages:
https://www.pinterest.ca/medicalartsofficial/
https://www.facebook.com/Medicalartsofficial
https://www.youtube.com/@medic....alarts?sub_confirmat
https://www.instagram.com/medicalartsofficial/
https://www.tiktok.com/@medicalarts
This video and associated content are for entertainment and educational purposes only!!
Open Appendectomy Surgery Video
"How to Perform a Transthoracic Echocardiographic Study Volume 1: Transducer Position and Anatomy" is an instructional video, offered by ASE, and can be used for professional lectures and offers an interactive section for flexible presentations. The video includes an overview of relevant cardiac anatomy, a step by step presentation of all Transducer Positions, and the sequential transducer movements to acquire standard echo images needed to complete a Transthoracic Echocardiographic Study.

The video will describe what is oxygen saturation? What is Oxygen content and what is oxygen capacity. Please see my web site for disclaimer.

You may have heard that some positions, such as your partner on top (missionary position), are better than others for getting pregnant. In fact, there's no evidence to back these theories up. Experts just haven't done the research yet. What experts have done, though, is use scanning to show what's going on inside when you're doing the deed. The research looked at two positions: the missionary position and doggy style. (Doggy style being when you're on all fours, and your partner enters you from behind). Common sense tells us that these positions allow for deep penetration. This means that they're more likely to place sperm right next to your cervix (the opening of your uterus). The scans confirm that the tip of the penis reaches the areas between the cervix and vaginal walls in both of these positions. The missionary position allows the penis to reach the area at the front of the cervix. The rear entry position reaches the area at back of the cervix. It's amazing what some experts spend their time doing, isn't it! Other positions, such as standing up, or woman on top, may be just as good for getting sperm right next to the cervix. We just don't know yet. So, in the meantime, enjoy some variety in your sex life and keep it fun while you're trying for a baby. And talk to others who are hoping to get pregnant by joining our Actively trying group. Do I have to have an orgasm to conceive? Obviously, it's very important for your partner to reach orgasm if you are trying for a baby. There is no evidence, however, that you need to orgasm to conceive. The female orgasm is all about pleasure and satisfaction. It doesn't really help to get the sperm to the egg. Gentle contractions in your uterus can help the sperm along, but these happen without you having an orgasm. So, it's really not vital for you to reach orgasm after your partner, or even to reach orgasm at all, for you to conceive.

Learn what's working for other Nursing Students! Check out our Top 10 Most Popular Lessons Here: https://bit.ly/3nda5u3
Central Line Dressing Change- Nursing Skills
FREE Nursing School Cheat Sheets at: http://www.NURSING.com
Get the full PPE Donning & Doffing lesson here:
https://nursing.com/lesson/cen....tral-line-dressing-c
Welcome to the NURSING Family, we call it the most supportive nursing cohort on the planet.
At NURSING.com, we want to help you remove the stress and overwhelm of nursing school so that you can focus on becoming an amazing nurse.
Check out our freebies and learn more at: (http://www.nursing.com)
Central Line Dressing Change - Nursing Skills:
In this video we’re going to talk about central line dressing changes. In this particular video, we’re going to look at a PICC Line, but the same strategy is also used for a Central Line. Remember the dressing should be changed every 7 days or as needed for peeling or soiling
This includes PICC lines. Sterile technique must be maintained to prevent Central-Line Associated Bloodstream Infections (CLABSI)
We love you guys! Go out and be your best selves today! And, as always, happy nursing!
Bookmarks:
0.05 Introduction
0.22 Mask application
0:36 Patient positioning
0:48 Dressing removal
1:20 Sterilization
1:26 Dressing change kit
2:14 Sterile gloves (Lesson link below)
https://nursing.com/lesson/ski....lls-01-04-sterile-gl
2:50 Cleaning the site
3:30 Bio patch application
4:20 Changing infusion caps
4:41 Labeling the dressing
5:00 Outro
Visit us at https://nursing.com/medical-disclaimer/ for disclaimer information.
NCLEX®, NCLEX-RN® are registered trademarks of the National Council of State Boards of Nursing, INC. and hold no affiliation with NURSING.com.

Diagnosis of this condition is based on clinical symptoms alone, as there are no diagnostic laboratory tests. In order to meet the criteria for Tourette syndrome, both motor and vocal tics must be present before the age of 21 , and the tics must occur many times a day for at least 12 months which is the case in this patient. Tourette syndrome is associated with several comorbid conditions, with attention-deficit hyperactivity disorder (ADHD) and obsessive compulsive disorder (OCD) the most common. OCD is therefore the condition this child is most at risk of developing in the future.

Testing for the four features of Gerstmann Syndrome in this patient with two separate left sided strokes (left frontoparietal ischaemic stroke followed by left posterior parietal haemorrhagic stroke). He exhibits (i) acalculia, (ii) agraphia, (iii) left-right disorientation, and (iv) finger agnosia. Complicating the issue is his obvious nonfluent aphasia (expressive dysphasia) with paraphasic errors (replacing words with associated words (e.g. says 'fork' instead of 'spoon')) and some comprehension issues.
Watch that Ectopic Pregnancy Baby Abortion Surgery
Watch that video of The World's Biggest Jigger Removal

heart dissection / cardiac anatomy

Demonstration of simple interrupted suturing technique for laceration repair.
