
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Other
Top videos
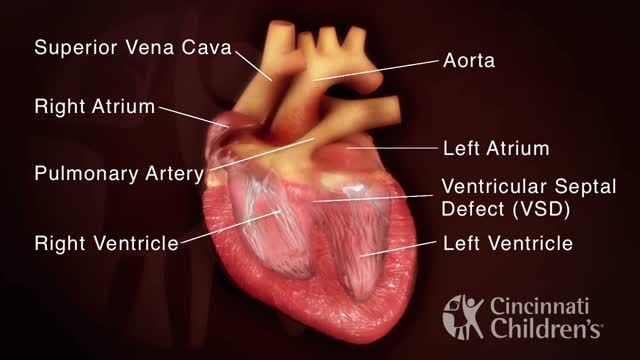

Tetralogy of Fallot (teh-TRAL-uh-jee of fuh-LOW) is a rare condition caused by a combination of four heart defects that are present at birth. These defects, which affect the structure of the heart, cause oxygen-poor blood to flow out of the heart and to the rest of the body. Infants and children with tetralogy of Fallot usually have blue-tinged skin because their blood doesn't carry enough oxygen. Tetralogy of Fallot is often diagnosed during infancy or soon after. However, tetralogy of Fallot might not be detected until later in life, depending on the severity of the defects and symptoms. With early diagnosis followed by appropriate surgical treatment, most children who have tetralogy of Fallot live relatively normal lives, though they'll need regular medical care and might have restrictions on exercise.

6 Weird Things That Happen To Us During Sleep
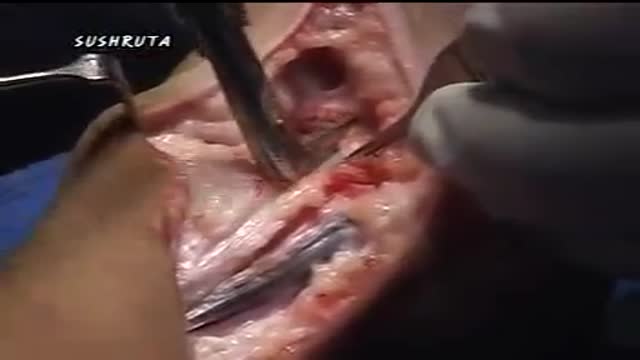
BACKGROUND: Clubfoot occurs in approximately one in 1000 live births and is one of the most common congenital birth defects. Although there have been several reports of successful treatment of idiopathic clubfoot with the Ponseti method, the use of this method for the treatment of other forms of clubfoot has not been reported. The purpose of the present study was to evaluate the early results of the Ponseti method when used for the treatment of clubfoot associated with distal arthrogryposis. METHODS: Twelve consecutive infants (twenty-four feet) with clubfoot deformity associated with distal arthrogryposis were managed with the Ponseti method and were retrospectively reviewed at a minimum of two years. The severity of the foot deformity was classified according to the grading system of Diméglio et al. The number of casts required to achieve correction was compared with published data for the treatment of idiopathic clubfoot. Recurrent clubfoot deformities or complications during treatment were recorded. RESULTS: Twenty-two clubfeet in eleven patients were classified as Diméglio grade IV, and two clubfeet in one patient were classified as Diméglio grade II. Initial correction was achieved in all clubfeet with a mean of 6.9 +/- 2.1 casts (95% confidence interval, 5.6 to 8.3 casts), which was significantly greater than the mean of 4.5 +/- 1.2 casts (95% confidence interval, 4.3 to 4.7 casts) needed in a cohort of 219 idiopathic clubfeet that were treated during the same time period by the senior author with use of the Ponseti method (p = 0.002). Six feet in three patients had a relapse after initial successful treatment. All relapses were related to noncompliance with prescribed brace wear. Four relapsed clubfeet in two patients were successfully treated with repeat casting and/or tenotomy; the remaining two relapsed clubfeet in one patient were treated with extensive soft-tissue-release operations.

Every woman is different. So are her experiences of pregnancy. Not every woman has the same symptoms or even the same symptoms from one pregnancy to the next. Also, because the early symptoms of pregnancy often mimic the symptoms you might experience right before and during menstruation, you may not realize you're pregnant. What follows is a description of some of the most common early symptoms of pregnancy. You should know that these symptoms may be caused by other things besides being pregnant. So the fact that you notice some of these symptoms does not necessarily mean you are pregnant. The only way to tell for sure is with a pregnancy test.

SEX WITH DIAPHRAGM TO CONTROL UNWANTED PREGNANCY
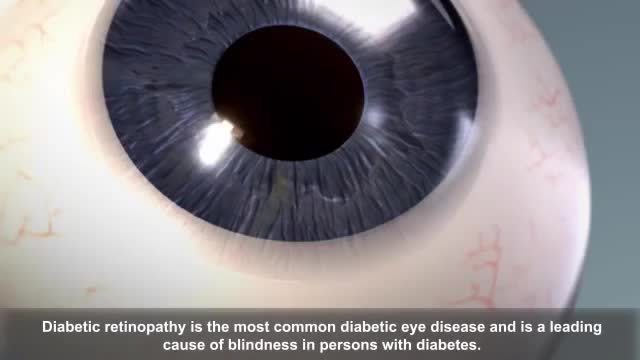
Diabetic retinopathy (die-uh-BET-ik ret-ih-NOP-uh-thee) is a diabetes complication that affects eyes. It's caused by damage to the blood vessels of the light-sensitive tissue at the back of the eye (retina). At first, diabetic retinopathy may cause no symptoms or only mild vision problems. Eventually, it can cause blindness. The condition can develop in anyone who has type 1 or type 2 diabetes. The longer you have diabetes and the less controlled your blood sugar is, the more likely you are to develop this eye complication.

Gastroparesis is a disorder affecting people with both type 1 and type 2 diabetes in which the stomach takes too long to empty its contents (delayed gastric emptying). The vagus nerve controls the movement of food through the digestive tract. If the vagus nerve is damaged or stops working, the muscles of the stomach and intestines do not work normally, and the movement of food is slowed or stopped. Just as with other types of neuropathy, diabetes can damage the vagus nerve if blood glucose levels remain high over a long period of time. High blood glucose causes chemical changes in nerves and damages the blood vessels that carry oxygen and nutrients to the nerves. - See more at: http://www.diabetes.org/living-with-diabetes/complications/gastroparesis.html?referrer=https://www.google.com/#sthash.rTgZiOuM.dpuf

Bronchiolitis is a common lung infection in young children and infants. It causes inflammation and congestion in the small airways (bronchioles) of the lung. Bronchiolitis is almost always caused by a virus. Typically, the peak time for bronchiolitis is during the winter months. Bronchiolitis starts out with symptoms similar to those of a common cold but then progresses to coughing, wheezing and sometimes difficulty breathing. Symptoms of bronchiolitis can last for several days to weeks, even a month.

The long-standing answer has been that sneezing is a reflex. When irritants — such as germs, dust, pollen, animal dander, or pollutants, just to name just a few — infiltrate the nose lining, the brain sends out a signal to get rid of it. That triggers a deep breath, which gets held in the lungs.

Cosmetic Eye and Eyelid Surgery
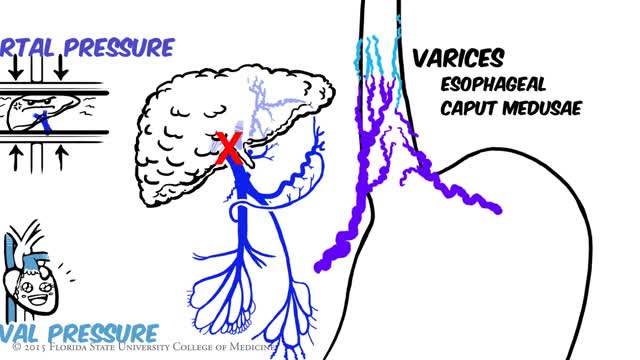
Portal hypertension is an increase in the blood pressure within a system of veins called the portal venous system. Veins coming from the stomach, intestine, spleen, and pancreas merge into the portal vein, which then branches into smaller vessels and travels through the liver.

-Korsakoff's syndrome is a common and preventable sequel of Wernicke's encephalopathy. Thiamine, if given during the stage of Wernicke's encephalopathy, can prevent the onset of Korsakoff's psychosis. The administration of glucose prior to thiamine can precipitate Korsakoff's syndrome, as seen in this case. In such patients, brain MRI frequently shows abnormal enhancement of the mammillary bodies & thallamus
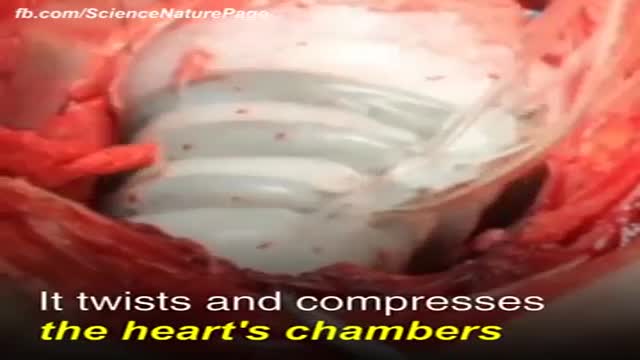
New Device can keep heart beating perfectly forever

Developmental Delay at Age 3 | Child Development

Orthognathic surgery presented in this video in order of appearance. 1. Advancement Genioplasty 2. Maxillary Advancement 3. Maxillary impaction 4. BSSO Mandibular Advancement 5. BSSO Mandibular Set-back 6. Maxillary Posterior Impaction

Risks & Benefits of Epilepsy Surgery | Epilepsy
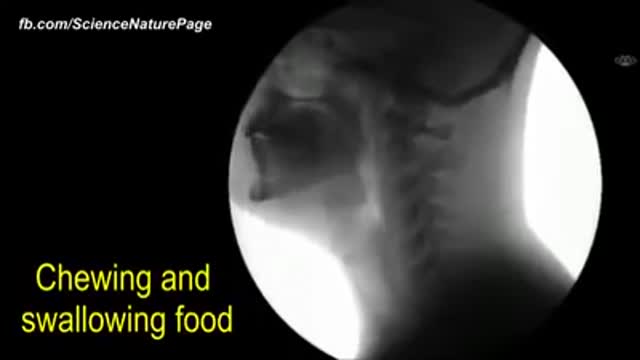
The human body as seen with MRI and X-RAY

#STOP VIOLENCE AGAINST DOCTORS#SAVE THE DOCTOR
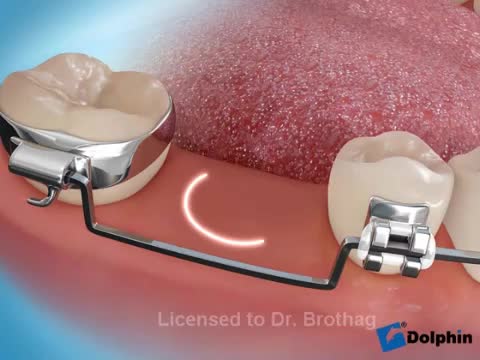
Aim: To detail two different clinical protocols and case studies using mini-implant anchorage developed to respond to certain clinical conditions. Methods: Two clinical protocols are described to upright mesially tilted mandibular molars. In the first protocol, a single mini-implant is inserted distally to the molar to be uprighted, and an elastic traction chain is applied to the tooth. In the second clinical approach, two mini-implants are inserted mesially. A screw-suspended TMA sectional archwire is applied (Derton-Perini technique). Two cases, descriptive of the two different treatment protocols, are described. In the first case, the mandibular right second premolar was missing and the adjacent first molar needed to be uprighted. A single screw was inserted distally to the first molar, and an elastic chain was applied. In the second case, the mandibular left second molar was missing and the third molar needed to be uprighted. Two mini-implants were inserted mesially and a fully screw-supported sectional archwire was used to upright and bodily mesialize the third molar. Results: Both uprighting approaches uprighted the molar axis without loss of anchorage. Conclusion: The two approaches to mandibular molar uprighting, developed as rational responses to different clinical cases, were both found to be effective. Research paper: Mandibular molar uprighting using mini-implants: Different approaches for different clinical cases-Two case reports.. Available from: https://www.researchgate.net/publication/224920305_Mandibular_molar_uprighting_using_mini-implants_Different_approaches_for_different_clinical_cases-Two_case_reports [accessed
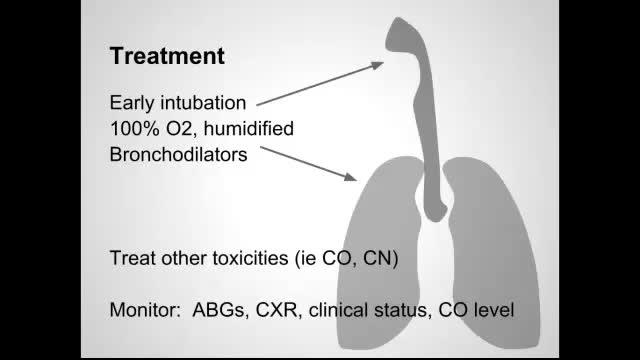
Smoke inhalation is the leading cause of death due to fires. It produces injury through several mechanisms, including thermal injury to the upper airway, irritation or chemical injury to the airways from soot, asphyxiation, and toxicity from carbon monoxide (CO) and other gases such as cyanide.
